The Greatest Medical Scandal

Excerpts from this incredibly accurate and revealing article by George Monbiot, originally published 12 March 2024

https://www.theguardian.com/commentisfree/2024/mar/12/chronic-fatigue-syndrome-me-treatments-social-services

‘You don’t want to get better’: the outdated treatment of ME/CFS patients is a national scandal

George Monbiot

George Monbiot

From harmful ‘therapies’ to social services referrals, the notion that this illness is psychosomatic is having devastating effects

You don’t want to get better’: the outdated treatment of ME/CFS patients is a national scandal

George Monbiot

“It’s the greatest medical scandal of the 21st century. For decades, patients with ME/CFS (myalgic encephalomyelitis/chronic fatigue syndrome) have been told they can make themselves better by changing their attitudes. This devastating condition, which afflicts about 250,000 people in the UK, was psychologised by many doctors and scientists, adding to the burden of a terrible physiological illness”

“Long after this approach was debunked in scientific literature, clinicians who championed it have refused to let go. They continue to influence healthcare systems, governments and health insurers. And patients still suffer as a result.”

“ME/CFS saps sufferers of energy and basic physical and cognitive functions, confining many to their homes or even their beds, often shutting down their working lives, social lives and family lives. The extreme seriousness of this condition, and the fact that there is neither a diagnostic test nor a validated treatment, places a special duty of rigour on doctors and researchers. But patient care has been compromised, and useful research inhibited, by the lingering conviction of many practitioners that ME/CFS is “psychosocial”: driven by patients’ beliefs and behaviour.”

Similar Posts

  • |

    Disabled, Discharged and Disappearing from View

    By Long Covid Support and Long Covid Kids

    Vital Long Covid Clinics Closing Across the UK Despite Ongoing Need, New Research Warns

    A study by Long Covid Support and Long Covid Kids has unveiled alarming gaps in Long Covid care, revealing that numerous specialist services across the UK are either shutting down or facing imminent closure. Despite NHS England confirming funding for Long Covid services through 2025/26, Freedom of Information (FOI) requests and direct communications with service providers indicate that many are already closing or operating under uncertainty.

    This report explores the experiences of people with Long Covid in the UK in using NHS services. It views these experiences within the context of uncertainty around the future funding model from NHS England and the fragmented approaches to Long Covid care in the devolved nations. We use information from
    a number of sources to challenge the view that it is appropriate to
    de-prioritise specialist Long Covid services in the UK.

    Who this report is for
    This report is intended for policymakers and government departments, including Department for Health and Social Care (DHSC), Department for Work and Pensions (DWP), Department for Education (DfE), the Health Select Committee, health secretaries, and the All-Party Parliamentary Group (APPG) on Long Covid.
    It is also relevant to National Health
    Service (NHS) health authorities such as NHS England, individual healthcare boards in

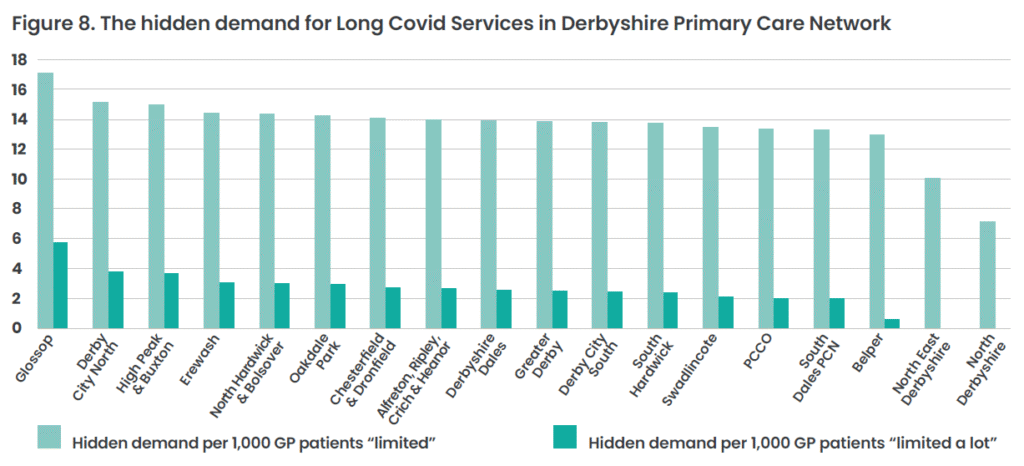
    This is a long read, but you have everything here. The “Hidden demand” figure on page 47 says for the Derbyshire case study shows that less demand for services isn’t the reason the services are closing down.

    View the full report online here:

    Disabled, Discharged and Disappearing from View

    The slides presented online are now included below:

    The slide pack is also available here

  • |

    Why Doctors don’t Reflect, collaborate, and listen

    Dr Rageshri Dhairyawan writes “Reflect, Collaborate and Listen” which examines why doctors don’t listen, and the urgent need to rebalance the power dynamic in the patient – doctor relationship.”

    See the full article here in the Lancet – It is free to download (after registration, which is quite easy).

    The abstract continues: “Anxieties about malingering or feigned illness are at least a thousand years old in the West”, argued public health ethicist Daniel S Goldberg in a paper on the history of “malingerers”. He gives several examples including Arnau de Vilanova who in the 13th century was so worried that patients were fooling him, by passing off other people’s urine samples as their own, that he wrote 19 pieces of advice for other physicians to spot the fraudulent. In this way, Goldberg shows how physicians have doubted the testimonies of patients for a very long time.

  • |

    ‘You don’t want to get better’: the outdated treatment of ME/CFS patients is a national scandal

    This article, published in March 2024 by George Monbiot analyses how medical gaslighting has stopped progress from being made to support people with the debilitating condition of ME/CFS


    Powered by Guardian.co.ukThis article titled “‘You don’t want to get better’: the outdated treatment of ME/CFS patients is a national scandal” was written by George Monbiot, for The Guardian on Tuesday 12th March 2024 08.00 UTC

    It’s the greatest medical scandal of the 21st century. For decades, patients with ME/CFS (myalgic encephalomyelitis/chronic fatigue syndrome) have been told they can make themselves better by changing their attitudes. This devastating condition, which afflicts about 250,000 people in the UK, was psychologised by many doctors and scientists, adding to the burden of a terrible physiological illness.

    Long after this approach was debunked in scientific literature, clinicians who championed it have refused to let go. They continue to influence healthcare systems, governments and health insurers. And patients still suffer as a result.

    ME/CFS saps sufferers of energy and basic physical and cognitive functions, confining many to their homes or even their beds, often shutting down their working lives, social lives and family lives. The extreme seriousness of this condition, and the fact that there is neither a diagnostic test nor a validated treatment, places a special duty of rigour on doctors and researchers. But patient care has been compromised, and useful research inhibited, by the lingering conviction of many practitioners that ME/CFS is “psychosocial”: driven by patients’ beliefs and behaviour.

    This was a story that found me. In 2021, after writing about long Covid, I was accused by the psychiatrist Prof Michael Sharpe of spreading it. Apparently, you could induce such illnesses by discussing them. Investigating further, I was astonished by the failure in his presentation to support his claim with evidence, and perturbed by his lack of satisfactory answers to my questions. Sharpe takes a similarly “biopsychosocial” approach to ME/CFS, one which at the time of his long Covid presentation still dominated medical practice in the UK.

    You can trace the origins of this model to a paper published in 1970. Without assessing a single patient or interviewing a single doctor, it blamed an earlier outbreak of post-viral ME/CFS on “mass hysteria” based on case notes alone. The reasoning included the fact that the outbreak affected more women than men. For centuries, doctors have been readier to classify women’s illnesses as hysterical or psychosomatic than they have men’s. ME/CFS, like long Covid, hits women harder, so, the thinking goes, it must be all in the mind.

    Freedom of information requests to the National Archives show how the biopsychosocial model became embedded in research practice and government policy. The minutes of a meeting on government benefits policy in 1993 give a sense of the position of the psychiatrist Simon Wessely at the time. As summarised in the minutes, he told the meeting that ME/CFS is “not a neurological disorder”. He reportedly claimed that apparently severe cases were likely to result from either a “misdiagnosed psychiatric disorder or poor illness management”, while many cases were “iatrogenic”: caused by medical examination or treatment. His views were apparently that “the worst thing to do is to tell them to rest”, “exercise is good for these patients”, “most cases can be expected to improve with time” and, perhaps most shockingly, “benefits can often make patients worse”.

    Every one of these claims now appears to be without foundation. But they became the basis of the dominant approach in this country to attempting to treat ME/CFS. The toll of patient suffering is hard to imagine.

    In 2007 this belief system became official guidance: the National Institute for Health and Care Excellence (Nice) advocated two treatments arising from the biopsychosocial model of the disease: graded exercise therapy (GET) and cognitive behavioural therapy (CBT). In 2011, a major study, the Pace trial, part-funded by the Department for Work and Pensions, claimed to show that GET and CBT were effective in treating ME/CFS. The study later turned out to be biased and profoundly flawed.

    The believers were championed by the Science Media Centre, of which (now Professor Sir) Simon Wessely was a founder member. Some of the media’s reporting, influenced by the centre, portrayed ME/CFS patients as abusive, threatening, workshy and resistant to treatment.

    As the doctrine spread through the medical profession, some practitioners adopted the same attitudes. A paper promoting psychological treatments lamented the “difficult challenge of … managing patients’ resistance to the treatment”, which arose from “lack of acceptance as to the rationale”. Nurses observed that “the patient should be grateful and follow your advice [but] the patient is quite resistant and there is this thing like you know, ‘The bastards don’t want to get better’.”

    We now know that patients were right to resist interventions that have proved to be both useless and harmful. The impacts were often horrific. A study in Switzerland found that the most powerful factor contributing to suicidal thoughts among people with ME/CFS was “being told the disease was only psychosomatic”.

    Some patients were forced into these treatment regimes, even locked in psychiatric units to make them comply. Some parents of children with ME/CFS were referred to social services for supposedly encouraging their belief that they were ill. Though unevidenced, the biopsychosocial model influenced the government’s social security policy, reinforcing its coercive treatment of people seeking disability benefits.

    In 2020, an independent review by Nice found that the quality of all the research promoting GET and CBT was either “low” or – mostly – “very low”. A paper reported that the thresholds in the 2011 Pace study at which patients were deemed to have recovered had been altered after the trial began. Several studies concluded that GET was actively harmful , as the exercise regime it promoted could worsen patients’ symptoms, causing post-exertional malaise. One paper reported that it was detrimental to the health of at least 50% of patients.

    As a result, in 2021 Nice concluded that GET and CBT should not be used to treat ME/CFS (though more conventional CBT can help patients with the psychological impacts of the illness). Similar shifts had already happened in the United States and the Netherlands. The condition is now correctly recognised as a physiological illness. Last month, a paper in the journal Nature Communications proposed a possible physiological mechanism for the condition.

    But some people never give up. Despite an overwhelming weight of evidence, the old believers, including Sharpe and Wessely, have continued to try to justify their model, obliging Nice recently to publish a strong refutation. Protected by powerful friends in the media, they could breathe life into their hypothesis long after it had been debunked. The new evidence-led thinking has yet to penetrate parts of the health system: some patients are still being mistreated.

    This is not how science should work. Beliefs should be based on evidence. In medicine, there is a double duty: respect the evidence and listen to patients. There is a psychological intervention that could improve the lives of people with ME/CFS: an apology and recognition of the harms they have suffered.

    • George Monbiot is a Guardian columnist

    • Join George Monbiot for a Guardian Live online event on Wednesday 8 May 2024 at 8pm BST. He will be talking about his new book, The Invisible Doctrine: The Secret History of Neoliberalism. Book tickets here

    • Do you have an opinion on the issues raised in this article? If you would like to submit a response of up to 300 words by email to be considered for publication in our letters section, please click here.

    • This article was amended on 12 March 2024 to replace an incorrect hyperlink.

    guardian.co.uk © Guardian News & Media Limited 2010

    Published via the Guardian News Feed plugin for WordPress.

  • | | | | |

    #Justice4ME Campaign Update No. 3

    Quote from Sarah Boothby on Social Media

    We have now taken legal advice, thanks to your donations, and instructed our lawyers to proceed with sending a letter before claim to the Department of Health and Social Care (DHSC).  This does not mean there will be a claim (an application to the court for Judicial Review of the Final Delivery Plan for ME/cfs) it means there are inconsistencies within the Plan that make it vulnerable to legal challenge.

    We doubt this vulnerability is what was intended in the drafting of the Plan.  We know people with ME/cfs have had cross party political support for decades.  We know hundreds of people contributed their knowledge, lived experience and expertise to developing the Plan, so we hope these snags will be resolved without a court hearing being necessary.  People living with ME, and the NHS staff trying their best to deliver safe clinical care without clear, succinct, safe clinical guidance to follow, deserve nothing less.

    If the reply from DHSC to our letter is not satisfactory, and the inconsistencies we have identified in the Final Delivery Plan persist, we must apply for Judical Review by 21 October at the latest.

    At this stage, we cannot share with you the advice we have been given but we will explain everything the very first chance we get.  Sorry if that’s frustrating; it is for us!  If the case does come to court the legal arguments will be made public that way but we hope the DHSC will make the changes needed sooner.  The changes needed are not huge, they are efficient, and they will not cost the NHS more money than is already being wasted on catastrophic mismanagement of ME.

    This is a first step, made possible only by your generosity and the long history of injustice that got us here.  We are honoroued by so many of you sharing your time, comments and money with us.  We could not have got so far without you.  We rely on your feedback on social media to be sure the aims of #Justice4ME reach the widest audience possible.

    More updates will follow in the coming weeks, including additional endorsements and images on our homepage.  Meanwhile, please keep on sharing our campaign with everyone you know, however unlikely!  Since we met the initial fundraising target in our launch week, the campaign to raise the final third for this first phase will continue throughout October.

    Thank you, thank you, thank you for helping make #Justice4ME a serious proposition. Let’s have our NHS knowing what to do about ME without doubts, indecision or delays – all over the UK, please.

    #JusticeforME

  • Karen, Emma and Oonagh talk about their campaign group #ThereForME

    Julie interviews our three #ThereForME heroes. A relaxed chat about how the campaign came to be, how they all met, how ideas for their campaign tend to crystallise. They talk about the the #FundThePlan initiative and how their campaign might grow in the future.

    Buzzfeed link provided above as well as Spotify, as it doesn’t currently require a subscription to listen. Listening via Spotify makes it easier to listen whilst doing something else on your browser or phone.

    Find all other episodes in this series here: Living with Long Covid

Leave a Reply