Norwegian study shows – ME patients rarely return to work

What can wage development before and after a G93.3 diagnosis tell us about prognoses for myalgic encephalomyelitis?

A Norwegian study has shown that patients diagnosed with ME typically decline permanently in terms of their earning capabilities, as illustrated below by the drop in their average wage income over a period starting 9 years before diagnosis in 2016, until 9 years later in 2025. Less than 6% maintained an income of at least median wages after diagnosis.

Nine years before diagnosis, the men earned slightly less than their controls. Wages in the men’s groups then started falling sharply towards Y0 and continued falling in the first year after (Y1). They then fell more gradually towards Y9. The women’s average wages 9 years before diagnosis were slightly below their female controls. The wages fell more sharply between 2 years before and 1 year after diagnosis, where they stabilized at a low level.

Fig. 3. Comparing group average wages for men and women 18–67 years old, diagnosed with G93.3, from 9 years before until 9 years after diagnosis (N = 6249) using 2009–2018 data to simulate values for the control group (N = 2739).

Abstract

Prognoses for persons affected by myalgic encephalomyelitis (ME) are rarely studied systematically. Existing studies are often based on smaller samples with unclear inclusion and subjective outcome criteria, and few look at wages as indicators of illness trajectories. This article considers how ME affects the wages and dependency on public transfers of people affected over time, especially in the period when the welfare authorities investigate eligibility for disability pension. We matched Norwegian population register data on 8485 working-age individuals diagnosed with G93.3 (postviral fatigue syndrome) from 2009 to 2018 with wage and transfer data and compared male and female cases to control groups. The G93.3 population’s wages fell sharply from around 3 years before diagnosis to 1 year after and stabilized at a low level. Public transfers started increasing several years before diagnosis and stabilized at a high level after. Few of those making no or very low income around the time of the diagnosis resumed earning moderate wages, and only exceptional cases returned to wages corresponding to median wages.

The full study is available here: What can wage development before and after a G93.3 diagnosis tell us about prognoses for myalgic encephalomyelitis?

The study was featured in a news article, written in Norweigan but if you are lucky, Google will translate it for you! https://www.forskning.no/helse-samfunn-sykdommer/nesten-ingen-me-pasienter-kommer-tilbake-i-jobb/2464548
Similar Posts

  • |

    Doctors As Patients

    YouTube Movie has been released exposing the experience of five doctors living with ME, Long Covid, Lyme Disease and other related conditions. The video is not primarily narrated in English, but has English Subtitles.

    “Five medical doctors open up about living with #PAIS/#IACC conditions like ME, #longCOVID, and chronic #Lyme. It’s a format that I believe has never been shown before, not just in the Netherlands but possibly worldwide! They speak candidly about their experiences with illness, what they were taught (or not taught) in medical school, and how that shaped their own treatment decisions—sometimes even leading to harm. They reflect on how becoming patients themselves radically changed their views on medicine, science, and what needs to change in healthcare. It’s raw, honest, and incredibly insightful—for medical professionals, researchers, politicians, and patients alike.”

  • Preprint – Incidence and Prevalence of Post-COVID-19 Myalgic Encephalomyelitis: A Report from the Observational RECOVER-Adult Study

    Published: 13 January 2025

    Suzanne D. Vernon PhD, Tianyu Zheng MS, Hyungrok Do PhD, Vincent C. Marconi MD, Leonard A. Jason PhD, Nora G. Singer MD, Benjamin H. Natelson MD, Zaki A. Sherif PhD, Hector Fabio Bonilla MD, Emily Taylor MA, Janet M. Mullington PhD, Hassan Ashktorab PhD, Adeyinka O. Laiyemo MD, Hassan Brim PhD, Thomas F. Patterson MD, Teresa T. Akintonwa BA, Anisha Sekar BA, Michael J. Peluso MD, Nikita Maniar MD, Lucinda Bateman MD, Leora I. Horwitz MD & Rachel Hess MD on behalf of the NIH Researching COVID to Enhance Recovery (RECOVER) Consortium

    Abstract

    Background

    Myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) may occur after infection. How often people develop ME/CFS after SARS-CoV-2 infection is unknown.

    Objective

    To determine the incidence and prevalence of post-COVID-19 ME/CFS among adults enrolled in the Researching COVID to Enhance Recovery (RECOVER-Adult) study.

    Design, Setting, and Participants

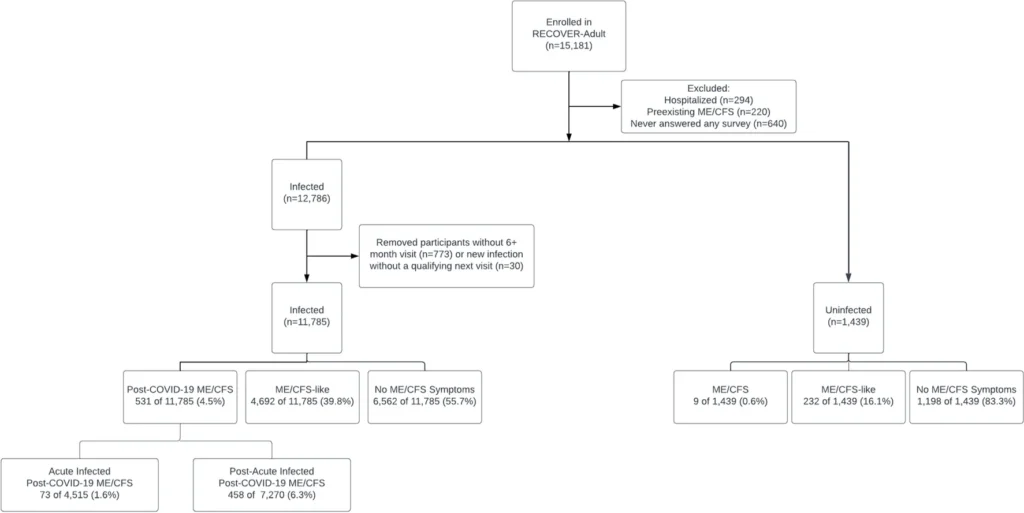
    RECOVER-Adult is a longitudinal observational cohort study conducted across the U.S. We included participants who had a study visit at least 6 months after infection and had no pre-existing ME/CFS, grouped as (1) acute infected, enrolled within 30 days of infection or enrolled as uninfected who became infected (n=4515); (2) post-acute infected, enrolled greater than 30 days after infection (n=7270); and (3) uninfected (1439).

    Measurements

    Incidence rate and prevalence of post-COVID-19 ME/CFS based on the 2015 Institute of Medicine ME/CFS clinical diagnostic criteria.

    Results

    The incidence rate of ME/CFS in participants followed from time of SARS-CoV-2 infection was 2.66 (95% CI 2.63–2.70) per 100 person-years while the rate in matched uninfected participants was 0.93 (95% CI 0.91–10.95) per 100 person-years: a hazard ratio of 4.93 (95% CI 3.62–6.71). The proportion of all RECOVER-Adult participants that met criteria for ME/CFS following SARS-CoV-2 infection was 4.5% (531 of 11,785) compared to 0.6% (9 of 1439) in uninfected participants. Post-exertional malaise was the most common ME/CFS symptom in infected participants (24.0%, 2830 of 11,785). Most participants with post-COVID-19 ME/CFS also met RECOVER criteria for long COVID (88.7%, 471 of 531).

    Limitations

    The ME/CFS clinical diagnostic criteria uses self-reported symptoms. Symptoms can wax and wane.

    Conclusion

    ME/CFS is a diagnosable sequela that develops at an increased rate following SARS-CoV-2 infection. RECOVER provides an unprecedented opportunity to study post-COVID-19 ME/CFS.

    Read the full preprint article here: https://link.springer.com/article/10.1007/s11606-024-09290-9

  • Large hippocampus detected in Long COVID and ME/CFS patients

    This study compared alterations in hippocampal subfields of 17 long COVID, 29 ME/CFS patients, and 15 healthy controls (HC), identifying significantly larger volumes in the left hippocampal subfields of both long COVID and ME/CFS patients compared to Healthy Controls.

    Abstract

    Long COVID and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS) patients share similar symptoms including post-exertional malaise, neurocognitive impairment, and memory loss. The neurocognitive impairment in both conditions might be linked to alterations in the hippocampal subfields. Therefore, this study compared alterations in hippocampal subfields of 17 long COVID, 29 ME/CFS patients, and 15 healthy controls (HC).

    Read More “Large hippocampus detected in Long COVID and ME/CFS patients”
  • Hidden Illness, Public Grief, and Research Funding: Why ME/CFS and Other Gradual-Onset Conditions Struggle for Recognition

    Author: Steve Fifield 3rd March 2026

    I wrote a simple draft paper on possible reasons why ME/CFS and similar conditions struggle so much for public recognition and funding.

    Executive Summary

    This briefing paper proposes that illnesses characterised by gradual onset, symptom invisibility, and ambiguous loss—such as Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS)—face structural disadvantages in public recognition and research funding.

    In contrast to diseases associated with sudden, catastrophic diagnoses (e.g., cancer, motor neurone disease, multiple sclerosis), ME/CFS often progresses gradually, without a singular crisis moment that mobilises families, media, and policymakers.

    Drawing on psychological research, communication theory, medical sociology, and health policy analysis, this paper outlines evidence supporting the hypothesis that acute grief catalyses mobilisation, while chronic ambiguity fosters adaptation rather than advocacy.

    1. Proposition Statement

    Public support for disease research funding is strongly influenced by emotional salience, narrative clarity, and visibility.

    • This paper proposes that:
    • Sudden, high-intensity diagnoses generate collective grief and advocacy mobilisation.
    • Gradual, invisible illness trajectories tend to produce adaptation and normalisation rather than public outrage.
    • Conditions lacking clear biomarkers or dramatic ‘trigger events’ may remain socially marginalised and underfunded.

    2. Psychological Evidence: Emotion, Grief, and Giving

    Research in behavioural psychology demonstrates that emotional intensity significantly influences charitable giving and advocacy behaviour.

    • Key evidence includes:
    • The ‘Identifiable Victim Effect’ shows individuals donate more readily when harm is concrete and personal (Small & Loewenstein, 2003).
    • Personal experience with illness strongly predicts sustained advocacy engagement (Bekkers & Wiepking, 2011).
    • Acute grief produces action-oriented coping responses, whereas ambiguous loss can lead to prolonged emotional adjustment rather than mobilisation (Boss, 1999).

    3. Media Visibility and Agenda Setting

    Agenda-setting research demonstrates that media coverage shapes public perceptions of issue importance (McCombs & Shaw, 1972).

    • Relevant dynamics:
    • Diseases with dramatic diagnostic narratives are more likely to receive concentrated media attention.
    • High-visibility campaigns (e.g., viral fundraising movements) significantly increase funding inflows.
    • Invisible or contested illnesses struggle to achieve sustained media framing as urgent biomedical crises.

    4. Medical Sociology: Invisible and Contested Illness

    ME/CFS has historically been classified as a contested or medically unexplained illness.

    • Sociological findings show:
    • Illnesses lacking objective biomarkers often face legitimacy challenges (Barker, 2008).
    • Symptom invisibility contributes to stigma and disbelief (Dickson et al., 2007).
    • Gradual functional decline may be socially normalised within families, reducing collective mobilisation.

    5. Research Funding and Disease Burden

    Multiple analyses indicate that biomedical research funding does not consistently align with disease burden.

    • Findings relevant to ME/CFS:
    • Funding levels for ME/CFS have historically been substantially lower than expected based on disability-adjusted life years (DALYs) (Dimmock et al., 2016).
    • Mortality salience and media visibility correlate more strongly with funding allocation than chronic disability alone.
    • Conditions perceived as life-threatening often secure greater political and philanthropic urgency.

    6. Policy and Strategic Implications

    If this proposition is valid, important implications follow for research institutions, advocacy organisations, and policymakers.

    • Potential strategies:
    • Develop narrative frameworks that communicate cumulative functional loss without sensationalism.
    • Align funding mechanisms more closely with disease burden metrics rather than media salience.
    • Invest in biomarker research to strengthen clinical legitimacy.
    • Promote public education campaigns that clarify the biological basis and severity of ME/CFS.

    Conclusion

    ME/CFS exemplifies how gradual-onset, invisible illnesses may be structurally disadvantaged within public funding ecosystems shaped by emotion, visibility, and narrative shock.

    Addressing this imbalance requires deliberate policy design, improved public communication, and recognition that chronic disability without dramatic rupture can be equally life-altering.

    Selected References

    1. Barker, K. (2008). Electronic support groups, patient-consumers, and medicalization.
    2. Bekkers, R., & Wiepking, P. (2011). A literature review of empirical studies of philanthropy.
    3. Boss, P. (1999). Ambiguous Loss: Learning to Live with Unresolved Grief.
    4. Dickson, A., et al. (2007). Stigma in chronic fatigue syndrome.
    5. Dimmock, M., et al. (2016). Estimating the disease burden of ME/CFS in the United States.
    6. McCombs, M., & Shaw, D. (1972). The agenda-setting function of mass media.
    7. Small, D., & Loewenstein, G. (2003). Helping a victim or helping the victim: Identifiable victim effect.
  • SequenceME DNA sequencing study gets £4.7m

    Follow-up project to DecodeME will analysye complete Genome sequences of 9000 ME/CFS existing samples to help pinpoint biology of ME and hopefully lead to treatments. Loads of detail in this article by Simon McGrath about how the DNA will be sequenced etc. using Oxford Nanopore technology.

    It is ME Awareness Day and I’ve had a tough one, so I’ll write a bit more soon… But didn’t want to forget documenting here what seems a major step in the right direction.

  • Post Vaccination Syndrome (PVS) preprint published by Yale University

    A preprint study from Yale University appears to identify individuals suffering from PVS with elevated levels of circulating isolated spike protein, compared to healthy controls, implying that the source is from a vaccine. Those studied had no prior history or evidence of a SARS-Cov2 infection.

    Researchers have since publication pointed out that Long Covid existed significantly before vaccines were available, defending suggestions from some that Long Covid had somehow been caused purely as a result of vaccination. This is not the case, and PVS forms a very small subset of those suffering with Long Covid Symptoms.

Leave a Reply