FundThePlan

  • Hidden Illness, Public Grief, and Research Funding: Why ME/CFS and Other Gradual-Onset Conditions Struggle for Recognition

    Author: Steve Fifield 3rd March 2026

    I wrote a simple draft paper on possible reasons why ME/CFS and similar conditions struggle so much for public recognition and funding.

    Executive Summary

    This briefing paper proposes that illnesses characterised by gradual onset, symptom invisibility, and ambiguous loss—such as Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS)—face structural disadvantages in public recognition and research funding.

    In contrast to diseases associated with sudden, catastrophic diagnoses (e.g., cancer, motor neurone disease, multiple sclerosis), ME/CFS often progresses gradually, without a singular crisis moment that mobilises families, media, and policymakers.

    Drawing on psychological research, communication theory, medical sociology, and health policy analysis, this paper outlines evidence supporting the hypothesis that acute grief catalyses mobilisation, while chronic ambiguity fosters adaptation rather than advocacy.

    1. Proposition Statement

    Public support for disease research funding is strongly influenced by emotional salience, narrative clarity, and visibility.

    • This paper proposes that:
    • Sudden, high-intensity diagnoses generate collective grief and advocacy mobilisation.
    • Gradual, invisible illness trajectories tend to produce adaptation and normalisation rather than public outrage.
    • Conditions lacking clear biomarkers or dramatic ‘trigger events’ may remain socially marginalised and underfunded.

    2. Psychological Evidence: Emotion, Grief, and Giving

    Research in behavioural psychology demonstrates that emotional intensity significantly influences charitable giving and advocacy behaviour.

    • Key evidence includes:
    • The ‘Identifiable Victim Effect’ shows individuals donate more readily when harm is concrete and personal (Small & Loewenstein, 2003).
    • Personal experience with illness strongly predicts sustained advocacy engagement (Bekkers & Wiepking, 2011).
    • Acute grief produces action-oriented coping responses, whereas ambiguous loss can lead to prolonged emotional adjustment rather than mobilisation (Boss, 1999).

    3. Media Visibility and Agenda Setting

    Agenda-setting research demonstrates that media coverage shapes public perceptions of issue importance (McCombs & Shaw, 1972).

    • Relevant dynamics:
    • Diseases with dramatic diagnostic narratives are more likely to receive concentrated media attention.
    • High-visibility campaigns (e.g., viral fundraising movements) significantly increase funding inflows.
    • Invisible or contested illnesses struggle to achieve sustained media framing as urgent biomedical crises.

    4. Medical Sociology: Invisible and Contested Illness

    ME/CFS has historically been classified as a contested or medically unexplained illness.

    • Sociological findings show:
    • Illnesses lacking objective biomarkers often face legitimacy challenges (Barker, 2008).
    • Symptom invisibility contributes to stigma and disbelief (Dickson et al., 2007).
    • Gradual functional decline may be socially normalised within families, reducing collective mobilisation.

    5. Research Funding and Disease Burden

    Multiple analyses indicate that biomedical research funding does not consistently align with disease burden.

    • Findings relevant to ME/CFS:
    • Funding levels for ME/CFS have historically been substantially lower than expected based on disability-adjusted life years (DALYs) (Dimmock et al., 2016).
    • Mortality salience and media visibility correlate more strongly with funding allocation than chronic disability alone.
    • Conditions perceived as life-threatening often secure greater political and philanthropic urgency.

    6. Policy and Strategic Implications

    If this proposition is valid, important implications follow for research institutions, advocacy organisations, and policymakers.

    • Potential strategies:
    • Develop narrative frameworks that communicate cumulative functional loss without sensationalism.
    • Align funding mechanisms more closely with disease burden metrics rather than media salience.
    • Invest in biomarker research to strengthen clinical legitimacy.
    • Promote public education campaigns that clarify the biological basis and severity of ME/CFS.

    Conclusion

    ME/CFS exemplifies how gradual-onset, invisible illnesses may be structurally disadvantaged within public funding ecosystems shaped by emotion, visibility, and narrative shock.

    Addressing this imbalance requires deliberate policy design, improved public communication, and recognition that chronic disability without dramatic rupture can be equally life-altering.

    Selected References

    1. Barker, K. (2008). Electronic support groups, patient-consumers, and medicalization.
    2. Bekkers, R., & Wiepking, P. (2011). A literature review of empirical studies of philanthropy.
    3. Boss, P. (1999). Ambiguous Loss: Learning to Live with Unresolved Grief.
    4. Dickson, A., et al. (2007). Stigma in chronic fatigue syndrome.
    5. Dimmock, M., et al. (2016). Estimating the disease burden of ME/CFS in the United States.
    6. McCombs, M., & Shaw, D. (1972). The agenda-setting function of mass media.
    7. Small, D., & Loewenstein, G. (2003). Helping a victim or helping the victim: Identifiable victim effect.
  • | | | | |

    #Justice4ME Campaign Update No. 3

    Quote from Sarah Boothby on Social Media

    We have now taken legal advice, thanks to your donations, and instructed our lawyers to proceed with sending a letter before claim to the Department of Health and Social Care (DHSC).  This does not mean there will be a claim (an application to the court for Judicial Review of the Final Delivery Plan for ME/cfs) it means there are inconsistencies within the Plan that make it vulnerable to legal challenge.

    We doubt this vulnerability is what was intended in the drafting of the Plan.  We know people with ME/cfs have had cross party political support for decades.  We know hundreds of people contributed their knowledge, lived experience and expertise to developing the Plan, so we hope these snags will be resolved without a court hearing being necessary.  People living with ME, and the NHS staff trying their best to deliver safe clinical care without clear, succinct, safe clinical guidance to follow, deserve nothing less.

    If the reply from DHSC to our letter is not satisfactory, and the inconsistencies we have identified in the Final Delivery Plan persist, we must apply for Judical Review by 21 October at the latest.

    At this stage, we cannot share with you the advice we have been given but we will explain everything the very first chance we get.  Sorry if that’s frustrating; it is for us!  If the case does come to court the legal arguments will be made public that way but we hope the DHSC will make the changes needed sooner.  The changes needed are not huge, they are efficient, and they will not cost the NHS more money than is already being wasted on catastrophic mismanagement of ME.

    This is a first step, made possible only by your generosity and the long history of injustice that got us here.  We are honoroued by so many of you sharing your time, comments and money with us.  We could not have got so far without you.  We rely on your feedback on social media to be sure the aims of #Justice4ME reach the widest audience possible.

    More updates will follow in the coming weeks, including additional endorsements and images on our homepage.  Meanwhile, please keep on sharing our campaign with everyone you know, however unlikely!  Since we met the initial fundraising target in our launch week, the campaign to raise the final third for this first phase will continue throughout October.

    Thank you, thank you, thank you for helping make #Justice4ME a serious proposition. Let’s have our NHS knowing what to do about ME without doubts, indecision or delays – all over the UK, please.

    #JusticeforME

  • | |

    All 72 Liberal Democrat MPs back resourcing of ME/CFS Delivery Plan

    Tessa Munt, officer of the APPG for ME, announced that 100% Liberal Democrat MPs have now signed a letter urging Wes Streeting and Ashley Dalton to back the ME/CFS Delivery Plan with the funding required to properly implement it.

    Tessa Munt – “I’m so delighted that all 72 LibDem MPs signed this letter to @wesstreeting @AshleyDalton_MP asking the govt to back the ME/CFS Delivery Plan with the resources it deserves. May this be a huge encouragement to the ME community and the start of meaningful change. #WorldMEDay”

  • |

    Disabled, Discharged and Disappearing from View

    By Long Covid Support and Long Covid Kids

    Vital Long Covid Clinics Closing Across the UK Despite Ongoing Need, New Research Warns

    A study by Long Covid Support and Long Covid Kids has unveiled alarming gaps in Long Covid care, revealing that numerous specialist services across the UK are either shutting down or facing imminent closure. Despite NHS England confirming funding for Long Covid services through 2025/26, Freedom of Information (FOI) requests and direct communications with service providers indicate that many are already closing or operating under uncertainty.

    This report explores the experiences of people with Long Covid in the UK in using NHS services. It views these experiences within the context of uncertainty around the future funding model from NHS England and the fragmented approaches to Long Covid care in the devolved nations. We use information from
    a number of sources to challenge the view that it is appropriate to
    de-prioritise specialist Long Covid services in the UK.

    Who this report is for
    This report is intended for policymakers and government departments, including Department for Health and Social Care (DHSC), Department for Work and Pensions (DWP), Department for Education (DfE), the Health Select Committee, health secretaries, and the All-Party Parliamentary Group (APPG) on Long Covid.
    It is also relevant to National Health
    Service (NHS) health authorities such as NHS England, individual healthcare boards in

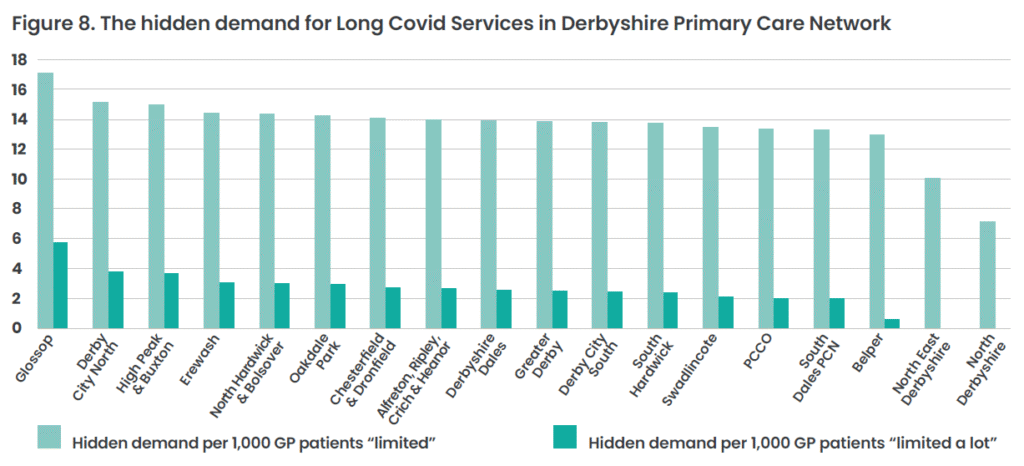
    This is a long read, but you have everything here. The “Hidden demand” figure on page 47 says for the Derbyshire case study shows that less demand for services isn’t the reason the services are closing down.

    View the full report online here:

    Disabled, Discharged and Disappearing from View

    The slides presented online are now included below:

    The slide pack is also available here

  • #ThereForME publishes first UK Ecosystem report for ME and Long Covid

    The #ThereForME team have published the first version of their UK Ecosystem Report for ME and Long Covid, created in collaboration with CrunchME. This report maps out key stakeholders and initiatives across the UK, aiming to inform advocacy efforts, policymakers, and potential funders of research and care.

    The report tracks active and future ME/CFS research projects within the UK. Following each overview slide like the one below, are detailed additional slides showing the technical nature of the work and interventions being trialled.

    Following slides go in to show research projects for Long Covid within the UK, Clinics and Clinicians, Biotech resource, and forthcoming conferences.

    The full UK ecosystem report for ME and Long Covid can be found here

    Everything about the #TherForME campaign can be found on the TherForME website

  • Karen, Emma and Oonagh talk about their campaign group #ThereForME

    Julie interviews our three #ThereForME heroes. A relaxed chat about how the campaign came to be, how they all met, how ideas for their campaign tend to crystallise. They talk about the the #FundThePlan initiative and how their campaign might grow in the future.

    Buzzfeed link provided above as well as Spotify, as it doesn’t currently require a subscription to listen. Listening via Spotify makes it easier to listen whilst doing something else on your browser or phone.

    Find all other episodes in this series here: Living with Long Covid