| |

Preprint – Smartphone-based monitoring of heart rate variability and resting heart rate predicts variability in symptom exacerbations in people with complex chronic illness

Annie Aitken1; Abbey Sawyer; Akiko Iwasaki; Harlan M. Krumholz; Rory Preston; Harry Leeming; Jenna Tosto-Mancuso; Amy Proal; Michael A. Osborne; David Putrino

Version 1 posted 29 Nov, 2024

Abstract

Background: Complex chronic conditions like Long COVID and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome involve energy limitations and changes in heart rate variability (HRV) and resting heart rate (HR). Mobile health technologies now offer real-time, valid measurements of HRV and HR, advancing symptom monitoring and management. Using a high-density dataset from an observational longitudinal study, we aimed to describe, quantify, and predict within-person co-variations in daily biometric data and subsequent crash, fatigue, and brain fog symptom occurrences.

Methods: Leveraging data collected through a mobile health app (n=4,244), we developed predictive models using mixed-effects linear regression and logistic regression to explore how within-person fluctuations in biometrics (HR, HRV, and respiratory rate) predict dynamic change in symptomology (crash, fatigue, and brain fog). Predictive performance was assessed using 5-fold stratified cross-validation and compared to a 20% holdout set to evaluate model generalizability to new observations and individuals.

Results: Across all symptom domains, within-person changes in HRV and HR consistently emerged as key predictors of symptom change across all models, with higher HR and lower HRV conferring risk for crashes, fatigue, and brain fog. Moreover, 7-day biometric stability (or variable dispersion) was a robust predictor of symptom occurrence and severity. Models trained solely on biometric features achieved moderate predictive performance in the stratified cross-validation set; however, incorporating random effects to capture individual-specific variations and prior-day symptom reports substantially enhanced model accuracy, with AUC values reaching .91.

Discussion and Conclusion: This study is the first to use data-driven models to predict everyday symptom experiences in individuals with complex chronic illnesses based on biometric fluctuations. Findings demonstrate the potential utility of mobile health tools for real-time monitoring of symptoms and highlight the need for further research to refine these predictive models and integrate them into clinical decision-making processes.

Read the full preprint article here: https://www.researchsquare.com/article/rs-5423422/v1
Similar Posts

  • Post Vaccination Syndrome (PVS) preprint published by Yale University

    A preprint study from Yale University appears to identify individuals suffering from PVS with elevated levels of circulating isolated spike protein, compared to healthy controls, implying that the source is from a vaccine. Those studied had no prior history or evidence of a SARS-Cov2 infection.

    Researchers have since publication pointed out that Long Covid existed significantly before vaccines were available, defending suggestions from some that Long Covid had somehow been caused purely as a result of vaccination. This is not the case, and PVS forms a very small subset of those suffering with Long Covid Symptoms.

  • Large hippocampus detected in Long COVID and ME/CFS patients

    This study compared alterations in hippocampal subfields of 17 long COVID, 29 ME/CFS patients, and 15 healthy controls (HC), identifying significantly larger volumes in the left hippocampal subfields of both long COVID and ME/CFS patients compared to Healthy Controls.

    Abstract

    Long COVID and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS) patients share similar symptoms including post-exertional malaise, neurocognitive impairment, and memory loss. The neurocognitive impairment in both conditions might be linked to alterations in the hippocampal subfields. Therefore, this study compared alterations in hippocampal subfields of 17 long COVID, 29 ME/CFS patients, and 15 healthy controls (HC).

    Read More “Large hippocampus detected in Long COVID and ME/CFS patients”
  • Preprint – Incidence and Prevalence of Post-COVID-19 Myalgic Encephalomyelitis: A Report from the Observational RECOVER-Adult Study

    Published: 13 January 2025

    Suzanne D. Vernon PhD, Tianyu Zheng MS, Hyungrok Do PhD, Vincent C. Marconi MD, Leonard A. Jason PhD, Nora G. Singer MD, Benjamin H. Natelson MD, Zaki A. Sherif PhD, Hector Fabio Bonilla MD, Emily Taylor MA, Janet M. Mullington PhD, Hassan Ashktorab PhD, Adeyinka O. Laiyemo MD, Hassan Brim PhD, Thomas F. Patterson MD, Teresa T. Akintonwa BA, Anisha Sekar BA, Michael J. Peluso MD, Nikita Maniar MD, Lucinda Bateman MD, Leora I. Horwitz MD & Rachel Hess MD on behalf of the NIH Researching COVID to Enhance Recovery (RECOVER) Consortium

    Abstract

    Background

    Myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) may occur after infection. How often people develop ME/CFS after SARS-CoV-2 infection is unknown.

    Objective

    To determine the incidence and prevalence of post-COVID-19 ME/CFS among adults enrolled in the Researching COVID to Enhance Recovery (RECOVER-Adult) study.

    Design, Setting, and Participants

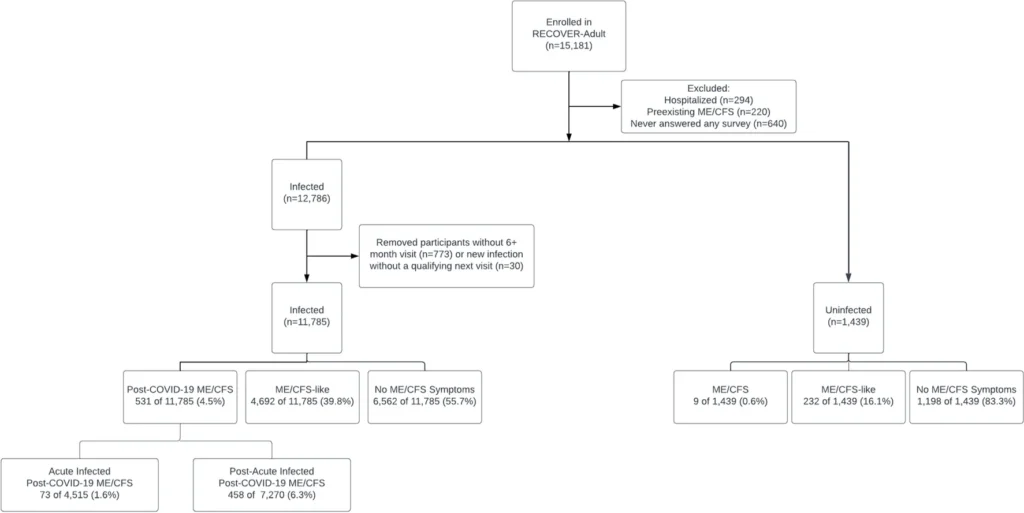
    RECOVER-Adult is a longitudinal observational cohort study conducted across the U.S. We included participants who had a study visit at least 6 months after infection and had no pre-existing ME/CFS, grouped as (1) acute infected, enrolled within 30 days of infection or enrolled as uninfected who became infected (n=4515); (2) post-acute infected, enrolled greater than 30 days after infection (n=7270); and (3) uninfected (1439).

    Measurements

    Incidence rate and prevalence of post-COVID-19 ME/CFS based on the 2015 Institute of Medicine ME/CFS clinical diagnostic criteria.

    Results

    The incidence rate of ME/CFS in participants followed from time of SARS-CoV-2 infection was 2.66 (95% CI 2.63–2.70) per 100 person-years while the rate in matched uninfected participants was 0.93 (95% CI 0.91–10.95) per 100 person-years: a hazard ratio of 4.93 (95% CI 3.62–6.71). The proportion of all RECOVER-Adult participants that met criteria for ME/CFS following SARS-CoV-2 infection was 4.5% (531 of 11,785) compared to 0.6% (9 of 1439) in uninfected participants. Post-exertional malaise was the most common ME/CFS symptom in infected participants (24.0%, 2830 of 11,785). Most participants with post-COVID-19 ME/CFS also met RECOVER criteria for long COVID (88.7%, 471 of 531).

    Limitations

    The ME/CFS clinical diagnostic criteria uses self-reported symptoms. Symptoms can wax and wane.

    Conclusion

    ME/CFS is a diagnosable sequela that develops at an increased rate following SARS-CoV-2 infection. RECOVER provides an unprecedented opportunity to study post-COVID-19 ME/CFS.

    Read the full preprint article here: https://link.springer.com/article/10.1007/s11606-024-09290-9

  • |

    Vagus Nerve Stimulation – Nurosym, Gammacore, Pulsetto and Sensate reviewed and compared

    A comprehensive overview of four VNS devices (though one doesn’t actually perform Vagus Nerve stimulation at all) by Health Scientific Institute.

    These devices have become popular, but they can also be very expensive, once monthly subscriptions are considered.

    People with ME and Long Covid should also take care to choose a device with a variable stimulation level, else stimulation given can cause unwanted side effects or unexpected increase of symptoms.

  • |

    Why Doctors don’t Reflect, collaborate, and listen

    Dr Rageshri Dhairyawan writes “Reflect, Collaborate and Listen” which examines why doctors don’t listen, and the urgent need to rebalance the power dynamic in the patient – doctor relationship.”

    See the full article here in the Lancet – It is free to download (after registration, which is quite easy).

    The abstract continues: “Anxieties about malingering or feigned illness are at least a thousand years old in the West”, argued public health ethicist Daniel S Goldberg in a paper on the history of “malingerers”. He gives several examples including Arnau de Vilanova who in the 13th century was so worried that patients were fooling him, by passing off other people’s urine samples as their own, that he wrote 19 pieces of advice for other physicians to spot the fraudulent. In this way, Goldberg shows how physicians have doubted the testimonies of patients for a very long time.

  • Norwegian study shows – ME patients rarely return to work

    What can wage development before and after a G93.3 diagnosis tell us about prognoses for myalgic encephalomyelitis?

    A Norwegian study has shown that patients diagnosed with ME typically decline permanently in terms of their earning capabilities, as illustrated below by the drop in their average wage income over a period starting 9 years before diagnosis in 2016, until 9 years later in 2025. Less than 6% maintained an income of at least median wages after diagnosis.

    Nine years before diagnosis, the men earned slightly less than their controls. Wages in the men’s groups then started falling sharply towards Y0 and continued falling in the first year after (Y1). They then fell more gradually towards Y9. The women’s average wages 9 years before diagnosis were slightly below their female controls. The wages fell more sharply between 2 years before and 1 year after diagnosis, where they stabilized at a low level.

    Fig. 3. Comparing group average wages for men and women 18–67 years old, diagnosed with G93.3, from 9 years before until 9 years after diagnosis (N = 6249) using 2009–2018 data to simulate values for the control group (N = 2739).

    Read More “Norwegian study shows – ME patients rarely return to work”

Leave a Reply


